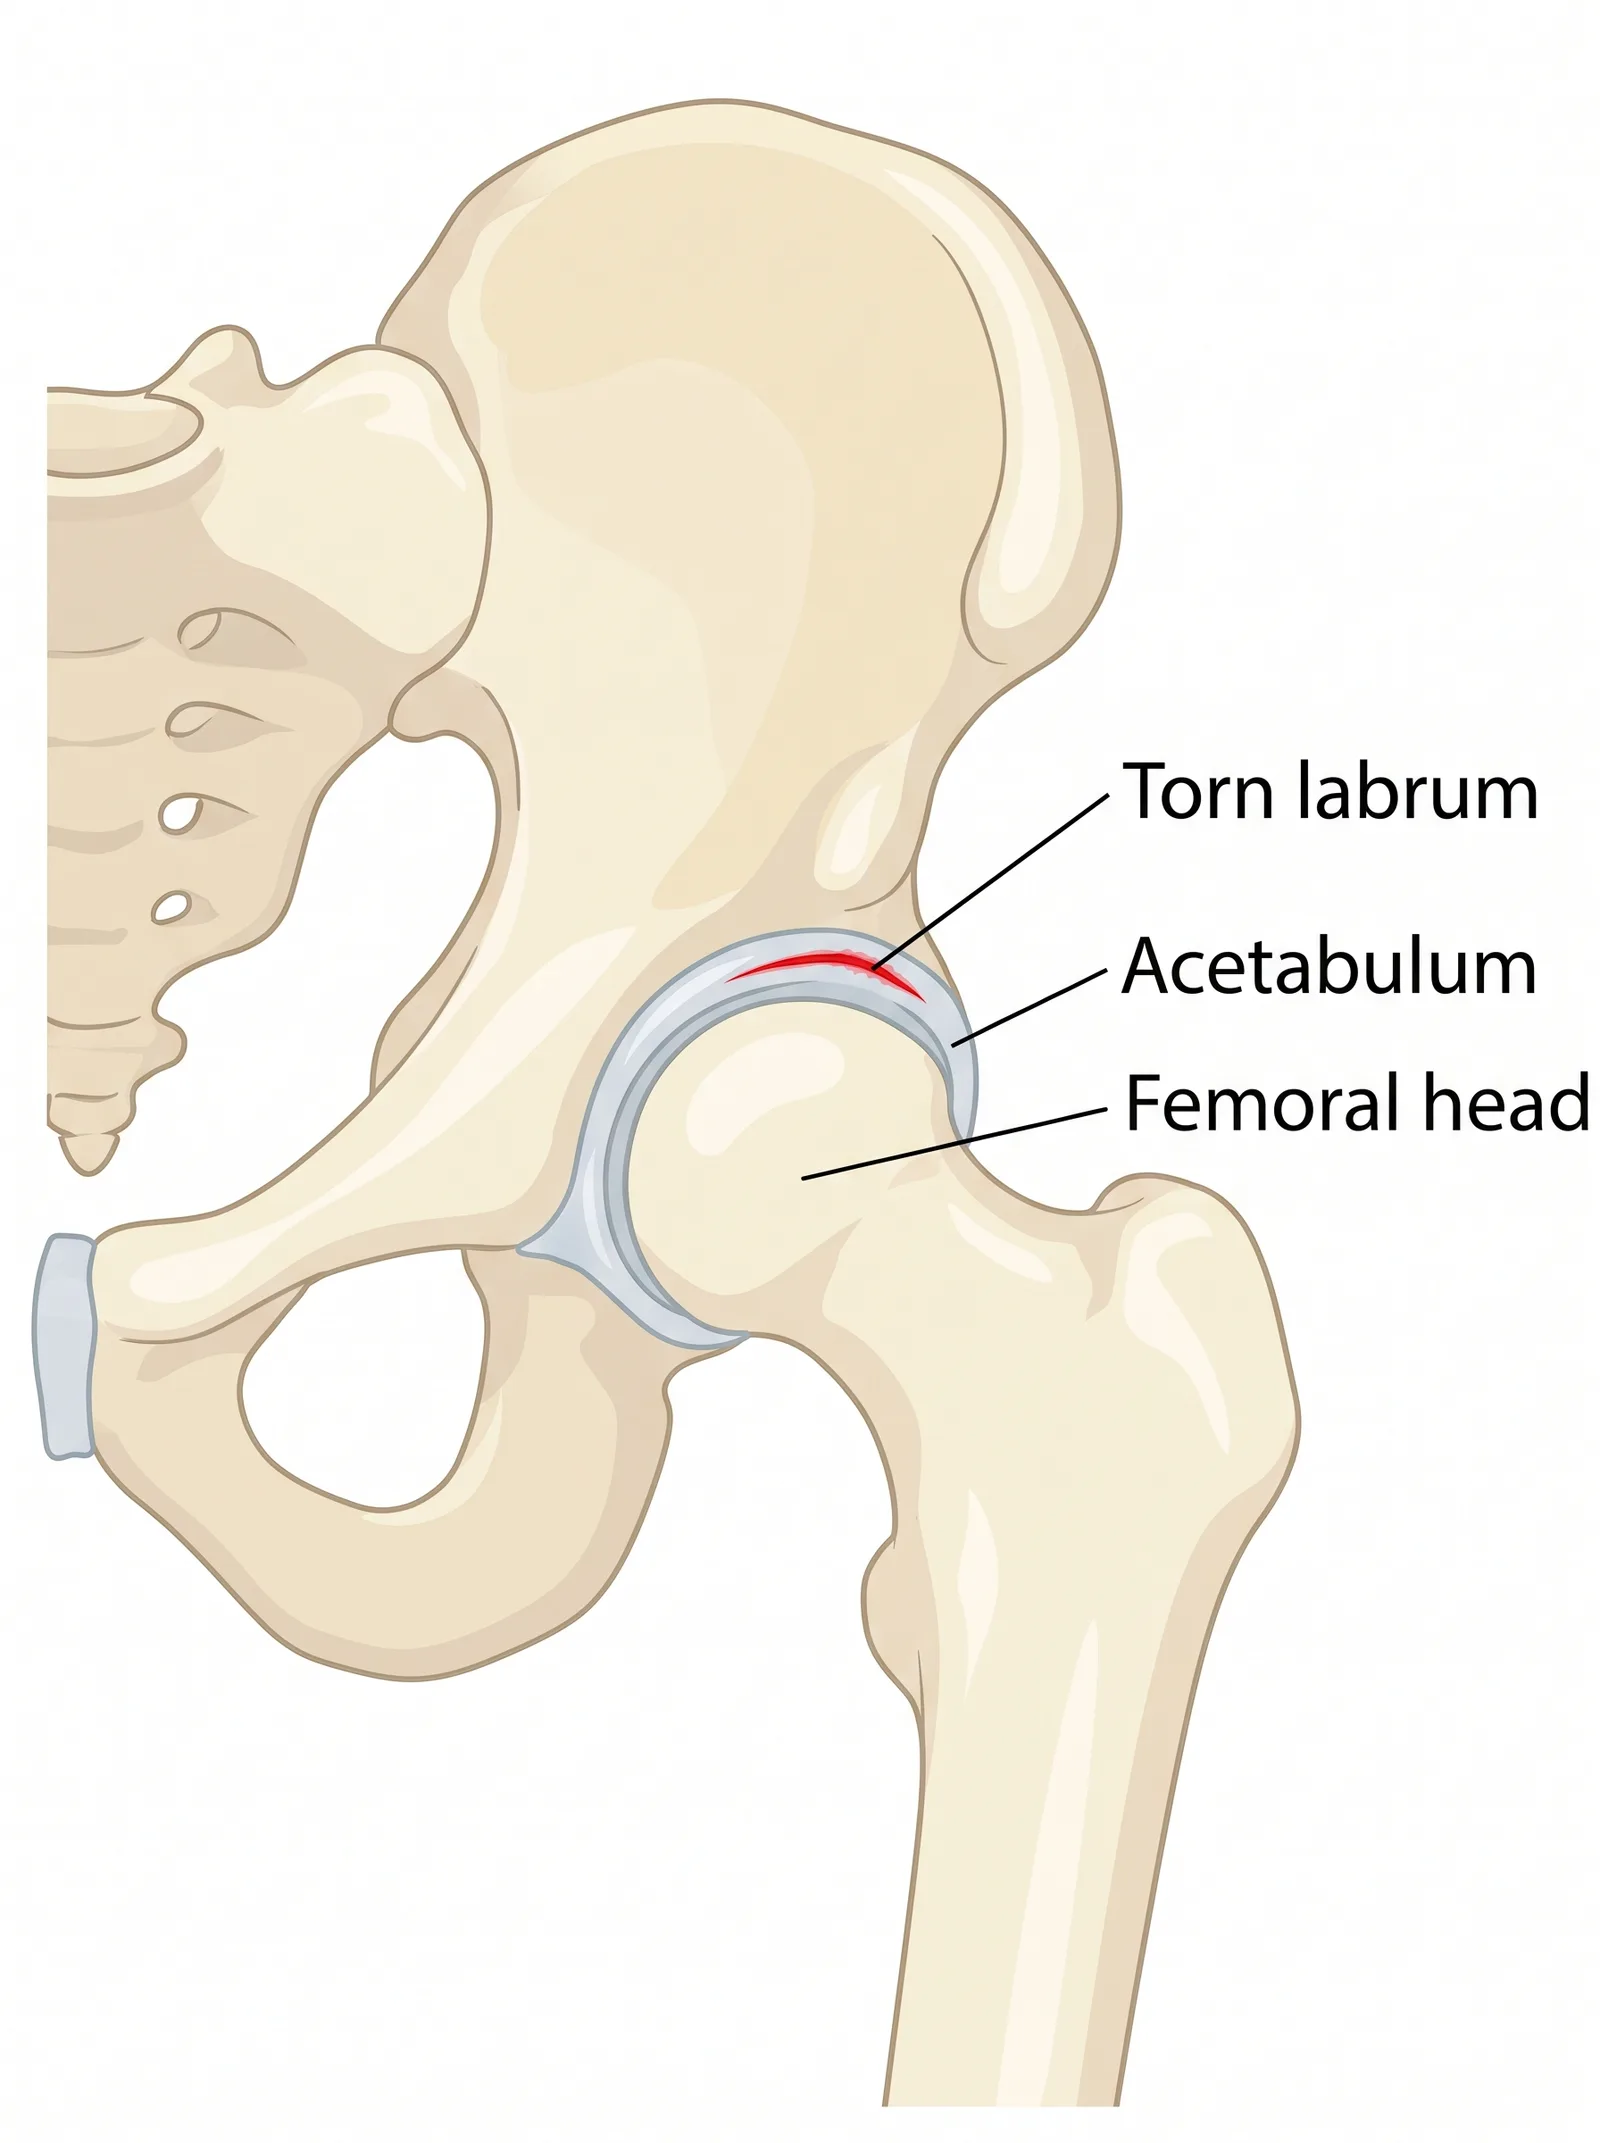
A hip labral tear is damage to the labrum, the ring of cartilage that lines the rim of the hip socket and helps hold the joint together. It can cause groin pain, catching or clicking, and stiffness, especially with pivoting or long sitting. Many tears improve with non-surgical care. Surgery is one option when they do not.
Shariff Bishai diagnoses and treats hip labral tear in Troy, from the first visit through recovery.
Who treats hip labral tear: a complete guide in Troy?
Shariff Bishai is a board certified orthopedic surgeon who treats hip labral tear: a complete guide in Troy, MI. Fellowship trained at Plancher Orthopaedics and Sports Medicine (orthopedic sports medicine fellowship). Dr. Bishai sees patients at the practice in Troy; appointments can be requested through this site.
What is a hip labral tear?
The hip is a ball-and-socket joint.
Around the rim of the socket runs a ring of firm cartilage called the labrum. Think of it as a gasket or a rubber seal at the edge of the cup. The labrum deepens the socket, helps keep the ball centered, and seals in a thin layer of fluid that lets the joint glide smoothly. A hip labral tear is a rip or fraying of that ring.
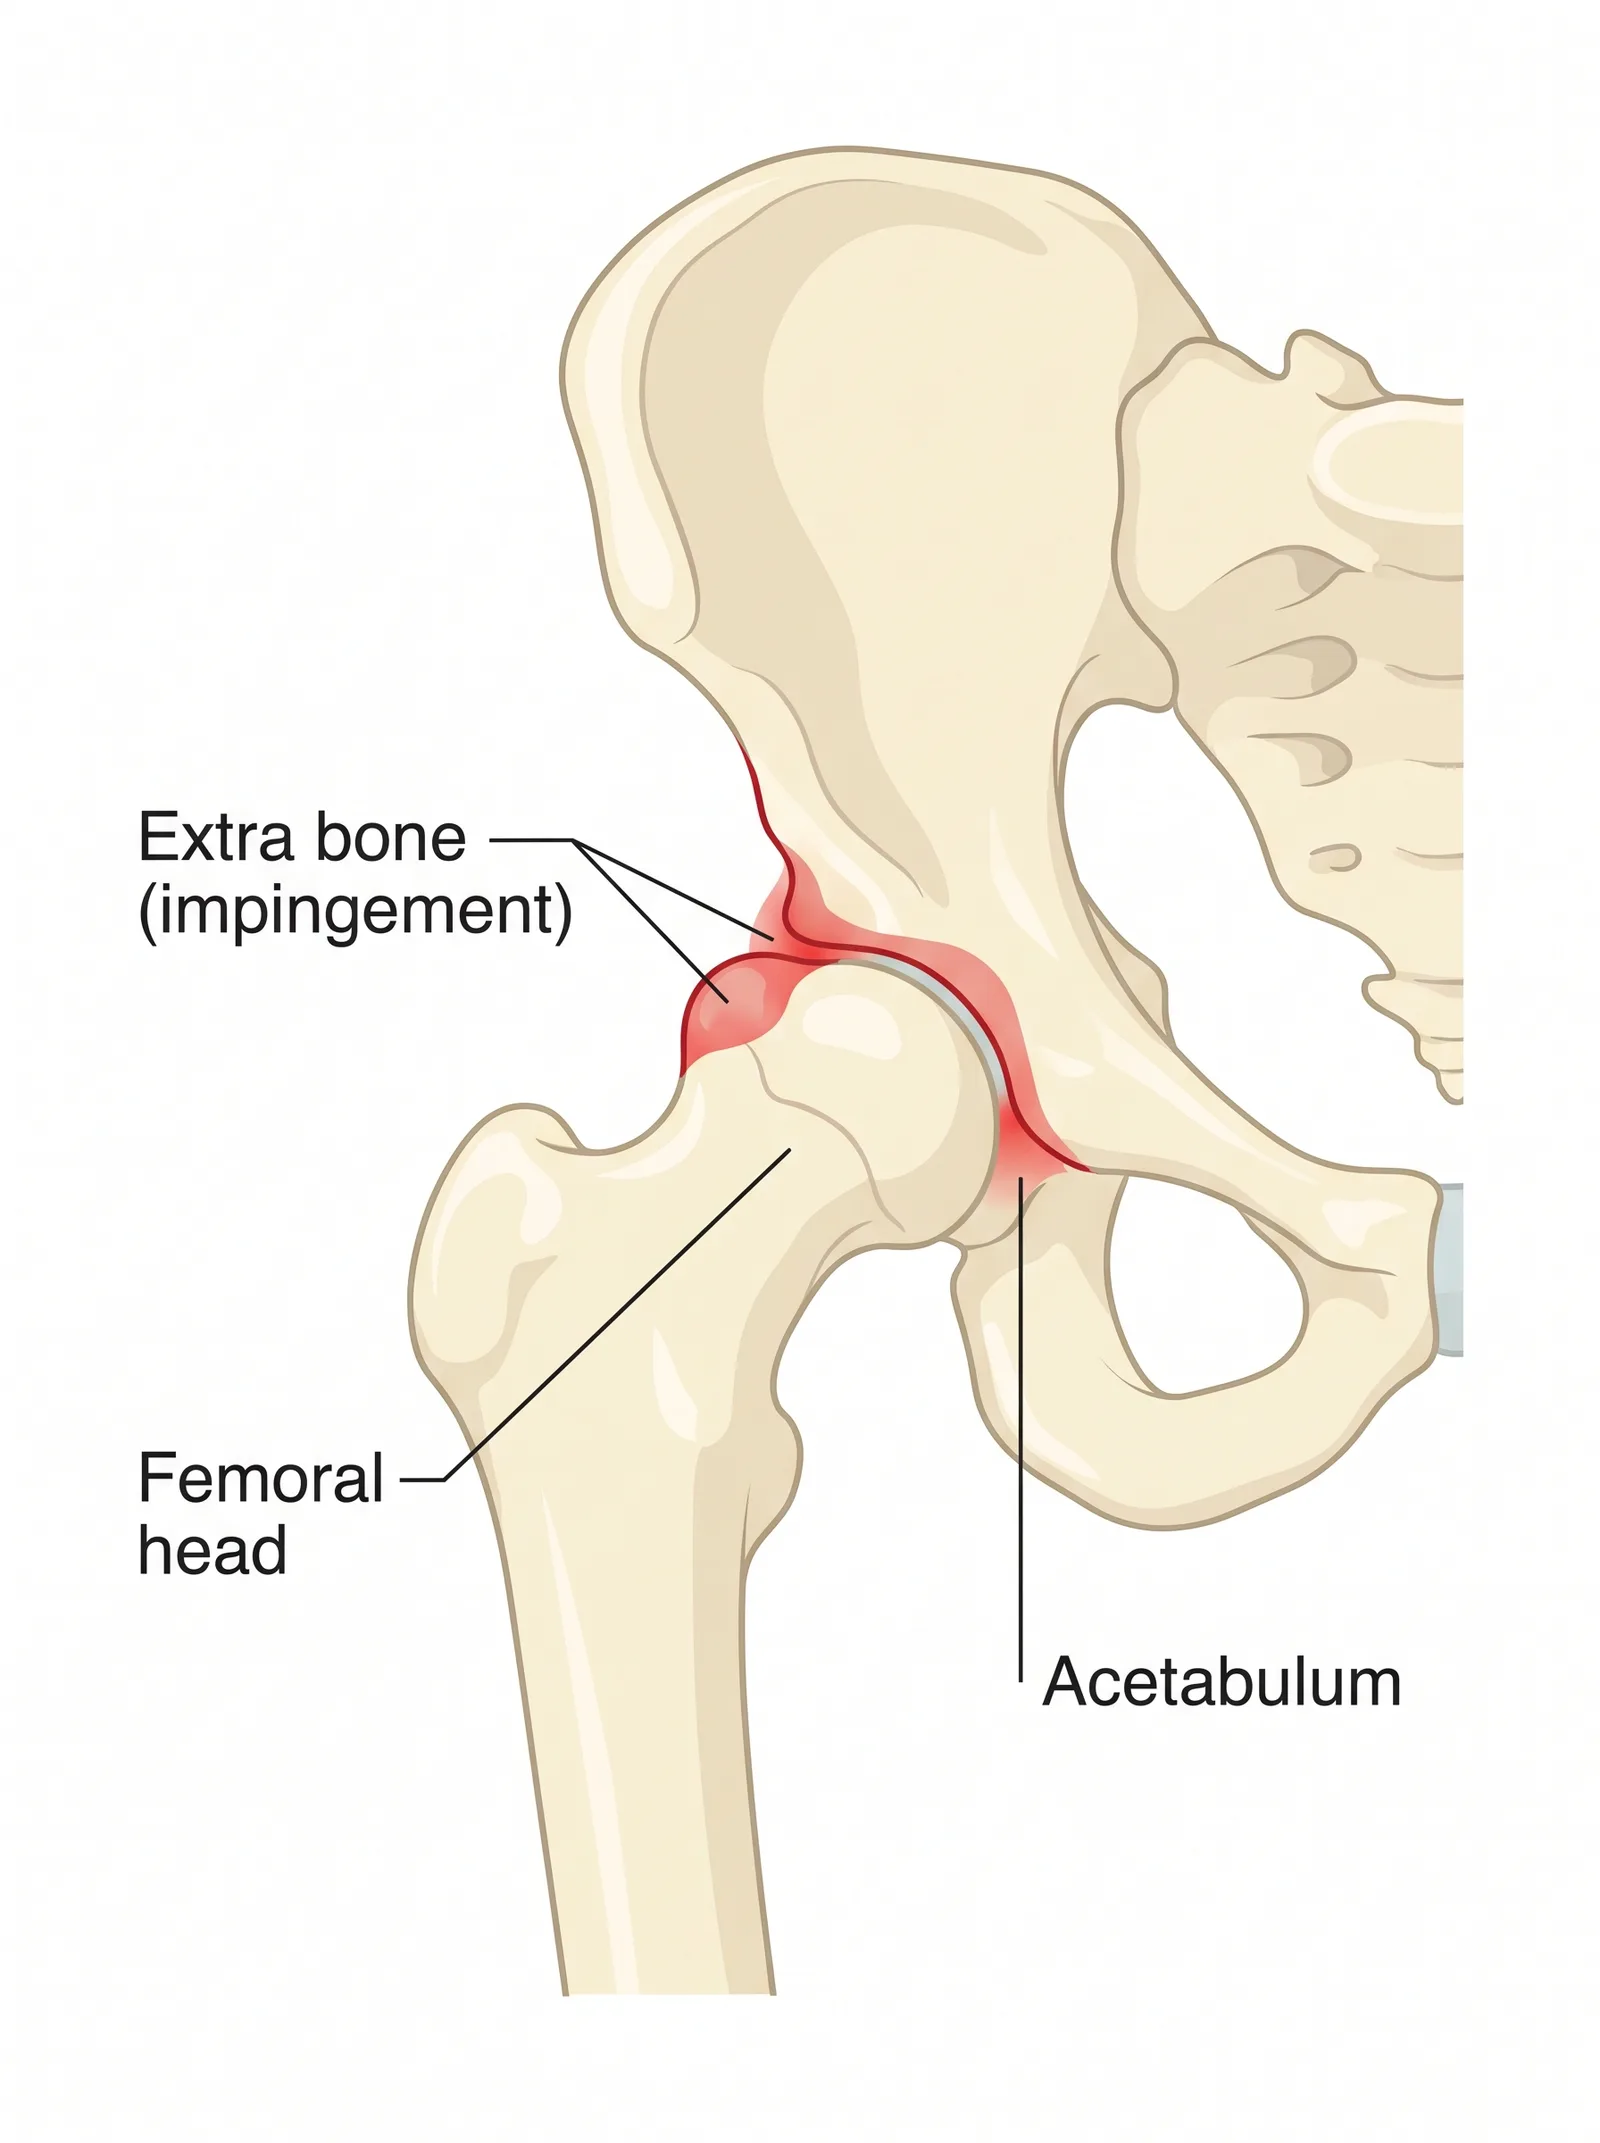
Tears happen for a few reasons. Some come from a specific injury, such as a twist, a fall, or a hard pivot in sports. Many others build up slowly from repeated motion, especially activities that involve deep bending or rotating of the hip. And a large share are linked to the shape of the hip itself. When the ball and socket do not fit together smoothly, the labrum takes extra stress and wears. Two shape problems in particular, femoroacetabular impingement and hip dysplasia, are closely tied to labral tears, and both have their own pages in this library.
The labrum has a limited blood supply, especially at its inner edge, which is part of why tears there do not always heal on their own. That does not mean every tear needs surgery. Many people have labral tears that cause little or no trouble, and many painful tears settle with non-surgical care. The point of treatment is to calm the symptoms and address what is stressing the labrum, not to chase every tear seen on a scan.
What are the symptoms of Hip Labral Tear, and when should you see a specialist?
A hip labral tear does not feel the same for everyone, and some tears cause no symptoms at all.
When symptoms do appear, people commonly describe.
- A deep ache or sharp pain in the groin or the front of the hip. - A catching, clicking, or locking feeling deep in the joint, as if something is briefly getting caught. - Pain that is worse with pivoting, twisting, or deep bending of the hip, and sometimes with long periods of sitting or driving. - Stiffness or a limited feeling in the hip's range of motion. - A sense that the hip is unstable or might give way, in some cases.
The pain often comes on gradually and lingers. Many people first notice it during or after activity, then find it creeping into everyday movements like getting out of a low chair or a car.
Reasons to see a specialist include groin or hip pain that has lasted more than a few weeks, catching or locking that keeps happening, or pain that is limiting your sport or your daily activity. Seeing a specialist does not mean surgery is coming. It means getting an accurate diagnosis, since hip pain has several possible sources, and starting with the gentlest care.
Some situations call for prompt attention: severe pain right after a fall or twist, an inability to bear weight, or a hip that locks and will not move. These should be evaluated quickly rather than watched.
How is Hip Labral Tear diagnosed, and what does the visit involve?
Diagnosing a labral tear takes a careful history, a hands-on exam, and usually imaging, because the symptoms overlap with other hip problems.
The visit starts with your story: where the pain sits, what movements bring it on, whether you feel catching, and whether a specific injury started it. Groin pain that worsens with pivoting and deep bending is a common pattern.
The exam includes moving the hip through specific positions. One common test brings the hip up, in, and rotated, which tends to reproduce the pain of a labral tear or impingement. The specialist will also check your range of motion and how you walk, and will look for other causes so the plan targets the right problem.
Imaging usually starts with X-rays. X-rays do not show the labrum itself, but they show the bones and can reveal the hip shapes that stress the labrum, such as impingement or dysplasia. The most useful test for the labrum is an MRI, a scan that shows soft tissue in detail. Often a specialist orders a specific version called an MR arthrogram, where a contrast dye is placed into the joint first to outline the labrum and make a tear easier to see.
One honest note: labral tears show up on scans in many people who have no pain at all. A tear on an MRI is only meaningful when it matches your symptoms and exam. This is why the diagnosis is built from the whole picture, not the scan alone. In some cases, a numbing injection into the joint is used to confirm the hip is the true source of pain.
What does treatment for Hip Labral Tear involve?
If non-surgical care does not resolve a labral tear, the most common surgical approach is hip arthroscopy, a procedure that uses a small camera and thin instruments through small incisions rather than one large opening.
This section explains the general sequence so you know what the path looks like. The decision to have surgery, and its details, are made with your surgeon.
- Anesthesia. Hip arthroscopy is usually done under general anesthesia, which means you are asleep, sometimes combined with a regional block that numbs the area for comfort afterward. - Positioning and access. The leg is gently positioned to open space within the joint. The surgeon makes a few small incisions, called portals, and inserts a tiny camera called an arthroscope along with slim instruments. - Viewing and confirming. The camera lets the surgeon see the labrum, the cartilage, and the joint surfaces directly, and confirm the tear and its pattern. - Treating the labrum. Depending on the tear, the surgeon either trims the damaged, frayed portion or repairs the labrum by reattaching it to the socket rim with small anchors and sutures. Repair aims to preserve the labrum's seal when the tissue allows. - Addressing the cause. If a bone shape is stressing the labrum, such as extra bone from impingement, the surgeon may reshape that bone during the same procedure so the joint moves without pinching. - Closing. The instruments are removed and the small incisions are closed. Most people go home the same day.
Hip arthroscopy is a detailed procedure, and not every labral tear is suited to it. Your surgeon will explain whether trimming or repair fits your tear, and what addressing any bone shape would involve.
What is the recovery timeline for Hip Labral Tear?
Recovery from a labral tear depends on whether you are healing with non-surgical care or after surgery.
For both, progress is most reliably measured by what you can do, alongside typical time ranges.
Non-surgical recovery is measured by capability: being able to sit, drive, and do daily tasks without the catching or deep ache, then returning to your sport or activity without a flare. Many people improve over several weeks to a few months of guided care, according to general guidance from the American Academy of Orthopaedic Surgeons. These are ranges, not promises.
Recovery after hip arthroscopy moves through stages defined by milestones:
- Protected phase: you use crutches and follow motion limits to protect the healing labrum. This early phase commonly lasts a few weeks, though the exact restrictions depend on whether the labrum was trimmed or repaired. - Motion and strength phase: with your surgeon's clearance, you move off crutches once you can bear weight comfortably and walk without a limp, and physical therapy shifts toward restoring strength and full motion. This often spans the following weeks to months. - Return-to-activity phase: you return to running, pivoting, and sport when strength, control, and motion meet your surgeon's and therapist's criteria, not simply when a date arrives. Full return to demanding activity commonly takes several months, according to general guidance from the American Academy of Orthopaedic Surgeons. These are ranges, not promises.
Repairs generally follow a more protective early schedule than trims. Your timeline depends on your tear, the surgery done, your health, and your rehabilitation.
How should you prepare for the visit or the procedure?
Preparing for the visit, if you have not yet been diagnosed: bring the history of your pain, what movements bring it on, what you have already tried, your other health conditions and medications, and your goals in plain terms.
Wear clothing that lets the hip be examined and lets you walk for the gait check. Bring any prior imaging or the name of the place that has it.
Preparing for hip arthroscopy, if surgery is planned, involves some logistics worth arranging ahead of time:
- Transportation. You cannot drive yourself home after anesthesia. Arrange for someone to drive you and, ideally, to stay with you the first night. - Crutches and home setup. You will likely use crutches for a period. Before surgery, clear walking paths, remove loose rugs, and set up a spot on one level where the things you need are within reach. - Time off. Plan time away from work based on your job. Desk work usually allows an earlier return than work that is on your feet or physically demanding. Your surgeon can help you estimate. - Help on hand. Have someone available to help with meals, errands, and getting around for the first several days. - A continuous passive motion machine or a stationary bike is sometimes recommended to keep the hip moving gently. Ask whether you will need one and how to get it.
If you have insurance questions about the visit, imaging, or a procedure, the office can answer those directly. Prices are handled by the office, not listed here.
Which warning signs should you call about?
After a diagnosis, and especially after surgery, some signs deserve a prompt call rather than waiting.
Call the office if you notice the following.
- Fever, or increasing redness, warmth, or drainage from an incision, which can point to infection. - Calf pain, swelling, or tenderness, especially with warmth, which can signal a blood clot. - Numbness, tingling, or weakness in the leg or foot that is new or getting worse. - Pain that is worsening rather than easing, or that is not controlled by your plan. - A hip that locks and will not move.
For chest pain, shortness of breath, or any symptom that feels severe or frightening, seek emergency care right away. For questions about your hip or your recovery, the office is the right first call, and the contact information is on the practice's contact page.
What results can you expect from Hip Labral Tear?
Outcomes for a labral tear depend on the tear, the underlying hip shape, and whether care is non-surgical or surgical.
- Many hip labral tears improve with non-surgical care, including activity changes and physical therapy, according to general guidance from the American Academy of Orthopaedic Surgeons. The degree of improvement varies from person to person. - When surgery is needed, hip arthroscopy for labral tears relieves pain and improves function for most appropriately selected patients, according to general information from the American Academy of Orthopaedic Surgeons. Results are better when any underlying bone shape driving the tear is also addressed. - Labral tears are commonly linked to hip conditions such as femoroacetabular impingement, according to general information from the American Academy of Orthopaedic Surgeons, which is why treatment looks at the cause and not the tear alone.
These figures describe groups of people, not a promise for one person. Your tear, your hip shape, your health, and your rehabilitation all shape your result. Your surgeon can put these ranges in the context of your own hip. These are ranges, not promises.
What do patients ask most?
Can a hip labral tear heal on its own?+
Do I need surgery for a labral tear?+
Why does my hip catch or click?+
Is a labral tear related to the shape of my hip?+
How long until I can return to sports after surgery?+
What are the treatment options?
- 01Activity changesStepping back from the movements that provoke the pain, especially deep bending, pivoting, and long sitting, often lowers symptoms and gives the joint a chance to settle.
- 02Physical therapyA physical therapist, a movement specialist, can strengthen the muscles around the hip and core, improve how the hip moves, and correct patterns that overload the labrum. For many people this is the core of non-surgical care.
- 03MedicationNonsteroidal anti-inflammatory drugs, often shortened to NSAIDs, can reduce pain and inflammation. They are not right for everyone, so the office can help you weigh them against your other health conditions.
- 04InjectionsA corticosteroid injection, a shot of anti-inflammatory medicine into the joint, can reduce pain and help confirm the hip as the source. Relief is temporary, but it can help you take part in therapy or get through a flare.
- 05Rest and gradual returnFor tears from a specific injury, a period of relative rest followed by a guided return to activity is often enough.
How do payments work?
Contact the office to confirm insurance participation.
Fellowship trained at Plancher Orthopaedics and Sports Medicine (orthopedic sports medicine fellowship). Sees patients in Troy.
About Dr. Bishai →